
CT
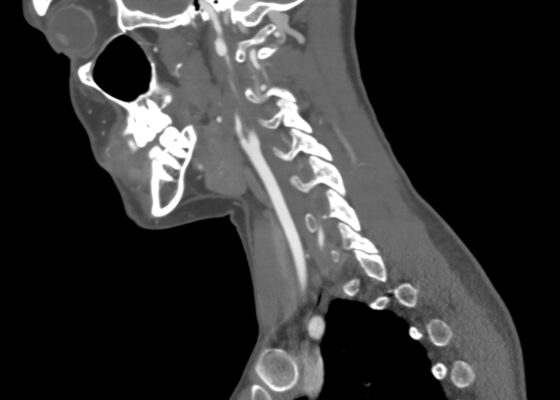

Blunt Cerebrovascular Injury: A Visual Case Report with Computed Tomography Angiography Findings Revealing Carotid and Vertebral Artery Dissection
DOI: https://doi.org/10.5070/M5.52229Computed tomography angiography of the neck showed worsening right ICA dissection with increased size of the pseudoaneurysm to 9 mm and worsening stenosis to greater than 70%. Computed tomography angiography of the neck also showed a new dissection of the V2 segment of the right vertebral artery with a 3 mm pseudoaneurysm and greater than 50% stenosis.
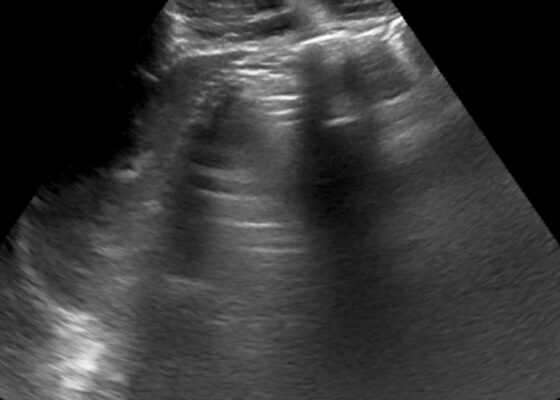
A-Lines below the Diaphragm – A Case Report of Occult Pneumoperitoneum
DOI: https://doi.org/10.5070/M5.52389The RUQ POCUS focusing over the left liver lobe shows multiple enhanced peritoneal stripe signs (red arrows) and several reverberation artifacts (yellow arrows). The second RUQ POCUS of the right lobe of the liver and the gallbladder shows reverberation artifacts (yellow arrow) and ring-down artifacts (blue arrow). The chest X-ray shows free air under the right diaphragm (orange arrow), which indicates pneumoperitoneum. The CT abdomen and pelvis show pneumoperitoneum near the porta hepatis (green arrow).
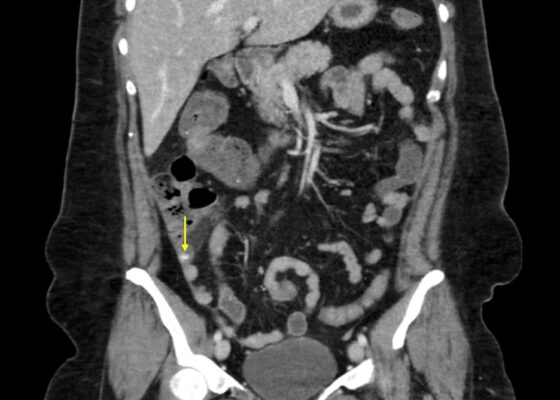
A Case Report of Acute Appendicitis Complicated by Appendicoliths
DOI: https://doi.org/10.5070/M5.52213Contrast-enhanced CT of the abdomen and pelvis was obtained. Coronal CT demonstrated a dilated appendix measuring up to 1.2 cm in diameter with multiple appendicoliths (yellow arrows), the largest measuring 1.1 cm. Mild periappendiceal fat stranding was present, consistent with acute appendicitis complicated by appendicoliths. The surrounding bowel and colon were normal in caliber and distribution. An additional coronal view demonstrated a dilated appendix (yellow arrow) containing an appendicolith with periappendiceal inflammatory changes. No evidence of perforation, abscess, or drainable fluid collection was identified.
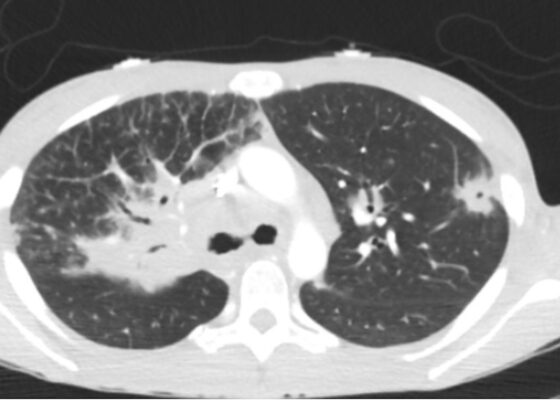
Case Report: Acute Dyspnea in a Young Female
DOI: https://doi.org/10.5070/M5.52254The patient underwent computer tomography (CT) imaging of the chest, abdomen, and pelvis. Computer tomography of the chest showed bilateral diffuse pulmonary nodules in a perilymphatic distribution (yellow arrows), and diffusely increased mediastinal and hilar soft tissue densities (blue circle), likely representing lymphadenopathy; a left upper lobe lesion with central cavitation (orange circle) was also seen likely to be associated with the same disease process as the extensive lymphadenopathy. Imaging of the abdomen and pelvis was significant for diffuse hypodensities of the liver and spleen suggesting a multi-system process.
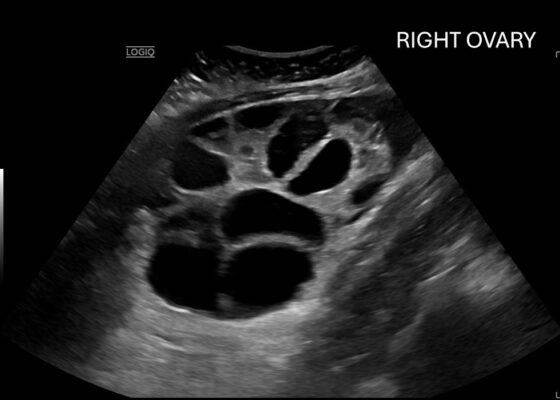
A Woman’s Infertility Journey Complicated by Severe Ovarian Hyperstimulation Syndrome – A Case Report
DOI: https://doi.org/10.5070/M5.52309Computed tomography (CT) of the abdomen and pelvis demonstrated pleural effusions in the lung bases (blue stars), ascites (blue stars), and enlarged ovaries with multiple cysts/follicles (white arrows). A formal pelvic US also demonstrated large volume ascites (white diamonds) and bilateral ovarian enlargement with numerous cysts. A CT angiogram (CTA) of the chest demonstrated small bilateral pleural effusions and no obvious pulmonary embolism.
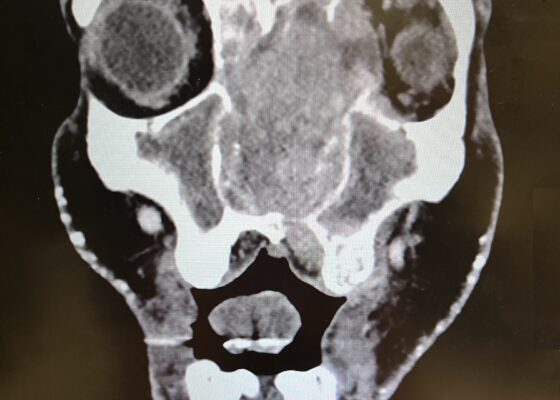
Diagnosis of Sinonasal Carcinoma in the Emergency Department: A Case Report Highlighting Red Flag Symptoms
DOI: https://doi.org/10.5070/M5.52257Physical exam revealed a gross deformity of the left side of the face with soft tissue swelling with no overlying skin changes. The left eye was proptotic and completely immobile, with cranial nerve (CN) 3, 4, and 6 palsies. Additionally, a large obstructive mass was noted in the left naris with resultant rightward displacement of the nasal septum. Intraocular pressures (IOPs) were measured to be 6 mmHg in the right eye and 11 mmHg in the left eye.
Imaging, including maxillofacial and neck soft tissue CTs revealed a large, destructive, soft tissue mass centered in the nasal cavity with significant osseous destruction of the midface and skull base (red highlighted area). There was mild intracranial extension with the mass abutting or infiltrating the inferior frontal lobes (green highlighted area). The nasal cavity and nasopharynx were obstructed (orange highlighted area). The mass invaded the left orbit with associated left-sided proptosis, left globe deformity, and compressed the left optic nerve and the left optic chiasm (blue arrows).
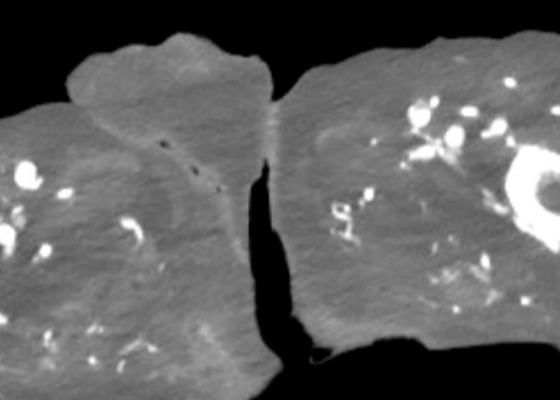
A Case Report of an Atypical Presentation of Fournier’s Gangrene
DOI: https://doi.org/10.5070/M5.52203A computed tomography (CT) scan of the abdomen and pelvis was significant for scrotal fluid and punctate gas locules (red arrow) without discrete evidence of invasion into the adjacent soft tissues, suspicious for Fournier’s gangrene. There was also fluid collection centered around the seminal vesicles suggestive of an abscess.
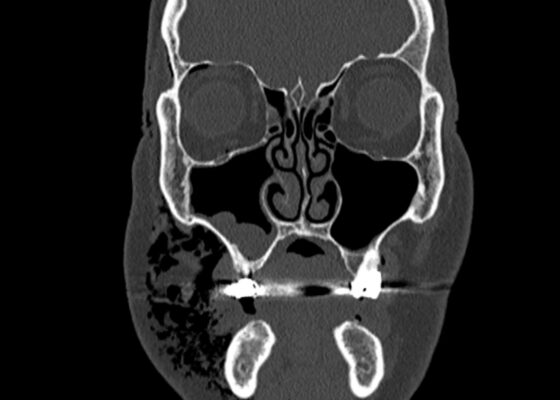
A Case Report of Facial Swelling and Crepitus Following a Dental Procedure
DOI: https://doi.org/10.21980/J83W8HGiven the physical exam findings of crepitus on the right neck up to the right lower eyelid, a maxillofacial CT scan without contrast was performed. It revealed diffuse subcutaneous air within the soft tissues of the face and neck and free air within the pre-septal soft tissue of the right eye, appearing as hyperlucent (dark) areas on CT within the soft tissue planes (blue outline). It showed no evidence of post-septal free air. A single-view chest X-ray was also performed and was unremarkable except for incompletely imaged soft tissue gas in the right lower neck (blue outline). On flexible fiberoptic laryngoscopy performed by ENT, the oropharynx appeared diffusely edematous and narrowed.