
Visual EM

A Low-Cost Rectal Foreign Body Removal Simulator
DOI: https://doi.org/10.5070/M5.56950This task trainer is intended to facilitate hands-on training in rectal foreign body removal. By the end of this training session, learners should be able to: 1) describe the indications and contraindications for rectal foreign body removal in the emergency department, and 2) demonstrate the ability to remove rectal foreign bodies of varying sizes, shapes, and depths of insertion using multiple techniques.
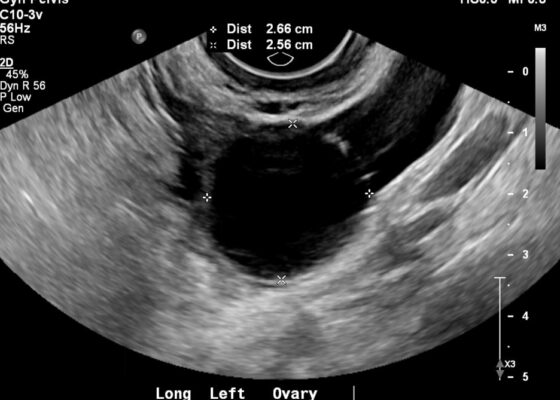

Ruptured Hemorrhagic Ovarian Cyst Mimicking Ruptured Ectopic Pregnancy in a Post-Transplant Patient: A Case Report
DOI: https://doi.org/10.5070/M5.52390A formal transvaginal ultrasound was ordered in the setting of the positive beta-hCG levels, which demonstrated a moderate volume of debris-containing free pelvic fluid layering in the posterior cul-de-sac (yellow highlighting), without sonographic evidence of an intrauterine gestational sac or yolk sac. Additionally, the left ovary contained a 2.8 cm cystic structure consistent with a hemorrhagic ovarian cyst (blue highlighting).
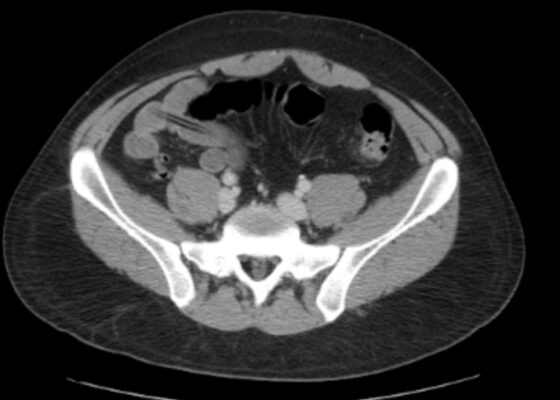
Intentional Pencil Ingestion – A Case Report of a Sharp Ingested Foreign Body
DOI: https://doi.org/10.5070/M5.53005Computerized tomography (CT) of the abdomen and pelvis two days after the ingestion of the pencil revealed a hypodense foreign object measuring 7.9 cm (blue arrows) in the lumen of the distal ileum. The images obtained demonstrate that the object progressed past physiological strictures within the gastrointestinal tract such as the esophagus and stomach; however, it had yet to progress through the ileocecal junction. Ingested foreign bodies carry a high risk of obstruction and perforation at these physiological stricture points. A repeat CT scan six days later showed that the pencil (yellow arrow) had progressed to the distal transverse colon.
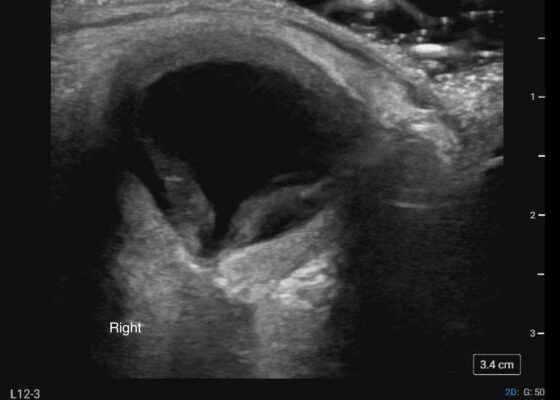
Case Report: Sonographic Detection of Chorionic Hemangiomas in Sturge-Weber Syndrome
DOI: https://doi.org/10.5070/M5.52314Ocular point-of-care ultrasound (POCUS) was performed using a linear 12-3 MHz probe on a Sonosite PX system. Examination of the symptomatic right eye revealed a complete retinal detachment. The detached retina appeared thickened, consistent with chronic detachment. Deep to the retina, the choroid was markedly thick with the widest portion observed in the posterior wall of the globe near the optic nerve. Sonographically, the choroid was isoechoic to the retina in the near field, hyperechoic to the retina in the far field (secondary to posterior acoustic enhancement) and homogenous. In the colorized image of the right eye, the red color denotes the choroid, labeled C, and the green color denotes the retina, labeled R. The left eye was also examined, shown in the last case image, and was grossly normal. No color doppler imaging was utilized for either eye. Optic nerve sheath diameter (ONSD) was 0.54 cm bilaterally.
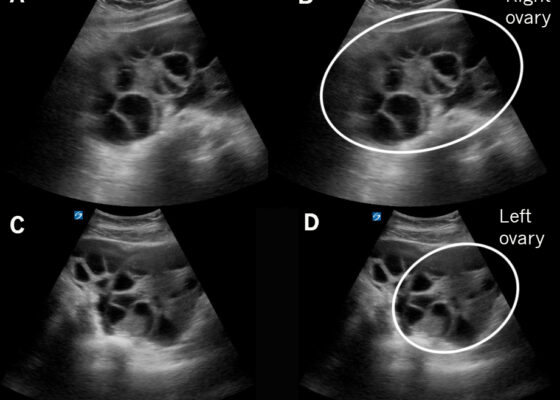
Point-of-Care Ultrasound Findings of Ovarian Hyperstimulation Syndrome: A Case Report
DOI: https://doi.org/10.5070/M5.52324Transabdominal POCUS in the right upper quadrant revealed clearly delineated pockets, the hypoechoic appearance being consistent with ascites, surrounding the liver and the gallbladder (Figure 1). A view of the left upper quadrant revealed a similar hypoechoic fluid collection that filled the space below the diaphragm and surrounded the spleen (Figure 2). A transabdominal pelvic view revealed enlarged ovaries, identifiable by the numerous, large, and well-delineated hypoechoic collections within that represent the enlarged follicles (Figure 3). The extent of the hypoechoic free fluid collections and the enlargement of the ovaries and their follicles is more apparent when viewed dynamically (Video).
Case Report: Atypical Presentation of Large Bowel Obstruction Due to Bezoar Formation in a Patient with a History of Colon Cancer
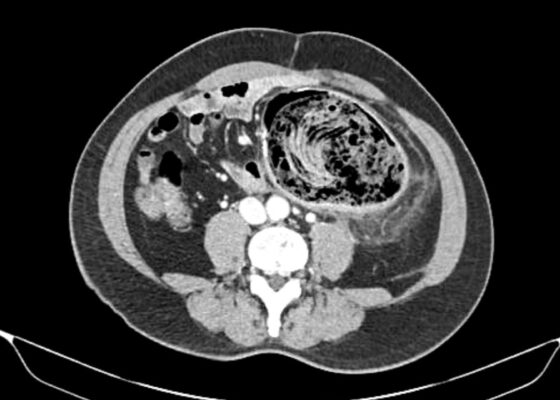
DOI: https://doi.org/10.5070/M5.53997CT with intravenous (IV) contrast revealed: (1) a large amount of fecal material in the descending colon at the level of anastomosis suggesting bezoar formation, (2) colonic wall thickening and inflammation suggestive of stercoral colitis, (3) abrupt caliber change at distal descending colon indicating partial large bowel obstruction, and (4) moderate to severe left hydronephrosis due to ureteropelvic junction obstruction with 0.4 cm calculus. No abscess or pneumatosis visualized. Annotated images demonstrate a large intraluminal mass at the descending colon anastomosis with associated abrupt caliber change (arrow), causing partial LBO and adjacent colonic wall inflammation (highlighted) consistent with stercoral colitis.
Case Report on Rare Presentation of Intravenous Leiomyomas with Intracardiac Leiomyomatosis
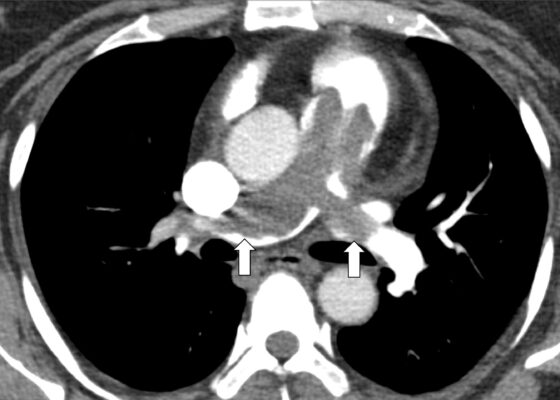
DOI: https://doi.org/10.5070/M5.52111Postoperatively, a CT of the abdomen and pelvis with contrast showed a lobulated soft tissue density (arrowheads) measuring 4.5 x 3 cm in the right pelvis. A subsequent MRI of the pelvis showed a 3.7 x 2.8 cm lobulated structure in the right pelvis above the vaginal cuff thought to be most consistent with an unusual cluster of venous structures. Following this, a CT venogram of the abdomen and pelvis revealed residual filling defects in the infrarenal IVC, extending through the right common iliac vein and multiple internal iliac branches.
A Rapidly Expanding Neck Mass with Risk of Airway Compromise: A Case Report
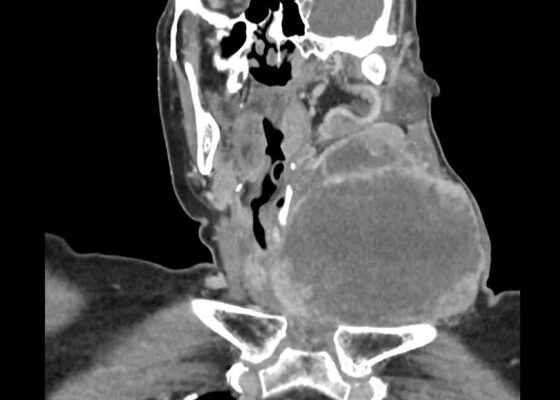
DOI: https://doi.org/10.5070/M5.52999Computed tomography (CT) scan of the neck soft tissue with contrast 15 days prior to current presentation demonstrated a centrally necrotic left thyroid mass measuring 10.1 cm and adjacent tumor thrombus within the adjacent left internal jugular vein extending superiorly to level of C1 without intracranial extension. There was regional mass effect with associated mild narrowing of the left common carotid artery and multiple additional lesions in right thyroid lobe, largest 2.9 cm. There was a necrotic left lower cervical lymph node of 1.1 cm with concern for nodal metastasis.