
Abdominal/Gastroenterology

A Low-Cost Rectal Foreign Body Removal Simulator
DOI: https://doi.org/10.5070/M5.56950This task trainer is intended to facilitate hands-on training in rectal foreign body removal. By the end of this training session, learners should be able to: 1) describe the indications and contraindications for rectal foreign body removal in the emergency department, and 2) demonstrate the ability to remove rectal foreign bodies of varying sizes, shapes, and depths of insertion using multiple techniques.
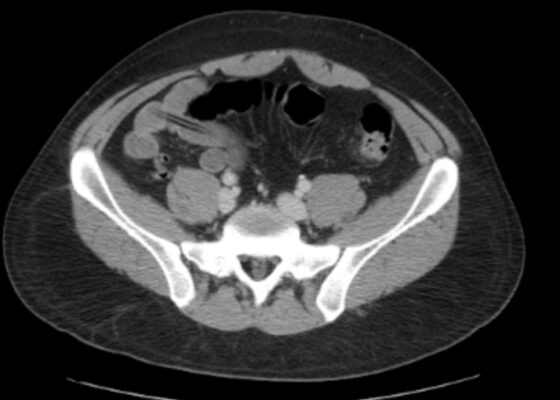

Intentional Pencil Ingestion – A Case Report of a Sharp Ingested Foreign Body
DOI: https://doi.org/10.5070/M5.53005Computerized tomography (CT) of the abdomen and pelvis two days after the ingestion of the pencil revealed a hypodense foreign object measuring 7.9 cm (blue arrows) in the lumen of the distal ileum. The images obtained demonstrate that the object progressed past physiological strictures within the gastrointestinal tract such as the esophagus and stomach; however, it had yet to progress through the ileocecal junction. Ingested foreign bodies carry a high risk of obstruction and perforation at these physiological stricture points. A repeat CT scan six days later showed that the pencil (yellow arrow) had progressed to the distal transverse colon.
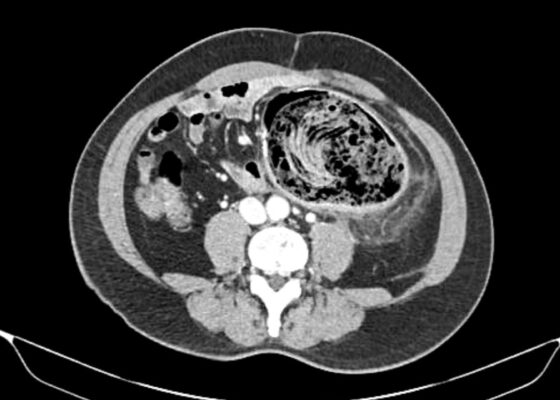
Case Report: Atypical Presentation of Large Bowel Obstruction Due to Bezoar Formation in a Patient with a History of Colon Cancer
DOI: https://doi.org/10.5070/M5.53997CT with intravenous (IV) contrast revealed: (1) a large amount of fecal material in the descending colon at the level of anastomosis suggesting bezoar formation, (2) colonic wall thickening and inflammation suggestive of stercoral colitis, (3) abrupt caliber change at distal descending colon indicating partial large bowel obstruction, and (4) moderate to severe left hydronephrosis due to ureteropelvic junction obstruction with 0.4 cm calculus. No abscess or pneumatosis visualized. Annotated images demonstrate a large intraluminal mass at the descending colon anastomosis with associated abrupt caliber change (arrow), causing partial LBO and adjacent colonic wall inflammation (highlighted) consistent with stercoral colitis.
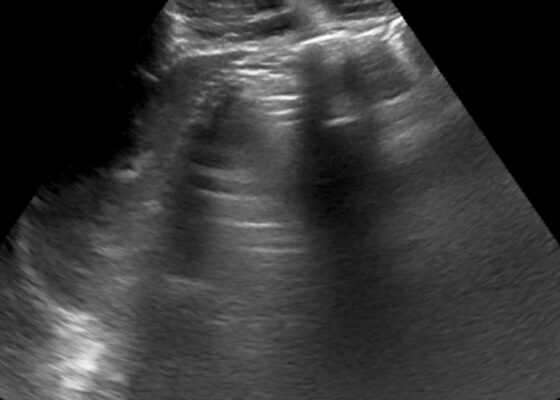
A-Lines below the Diaphragm – A Case Report of Occult Pneumoperitoneum
DOI: https://doi.org/10.5070/M5.52389The RUQ POCUS focusing over the left liver lobe shows multiple enhanced peritoneal stripe signs (red arrows) and several reverberation artifacts (yellow arrows). The second RUQ POCUS of the right lobe of the liver and the gallbladder shows reverberation artifacts (yellow arrow) and ring-down artifacts (blue arrow). The chest X-ray shows free air under the right diaphragm (orange arrow), which indicates pneumoperitoneum. The CT abdomen and pelvis show pneumoperitoneum near the porta hepatis (green arrow).
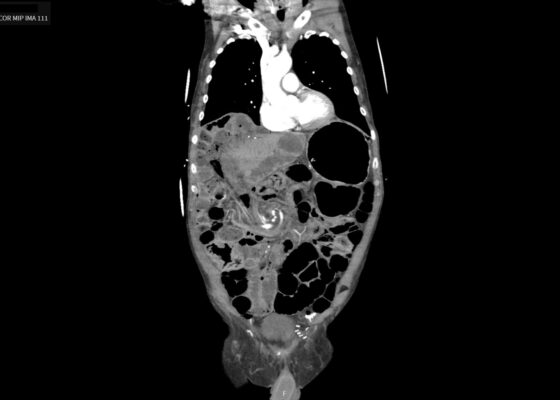
Caught in the Whirl: A Case Report of Midgut Volvulus in an Elderly Patient
DOI: https://doi.org/10.5070/M5.52361An upright chest x-ray demonstrated air underneath the diaphragm bilaterally (yellow arrows), enhancing the diaphragmatic contour. A computed tomography angiography (CTA) abdomen and pelvis showed scattered pneumoperitoneum (red arrow), dilated segments of small bowel (orange arrow), and clockwise swirling of the mesentery (blue arrow), concerning for mesenteric volvulus with possible bowel perforation.
A Case Report of Acute Appendicitis Complicated by Appendicoliths
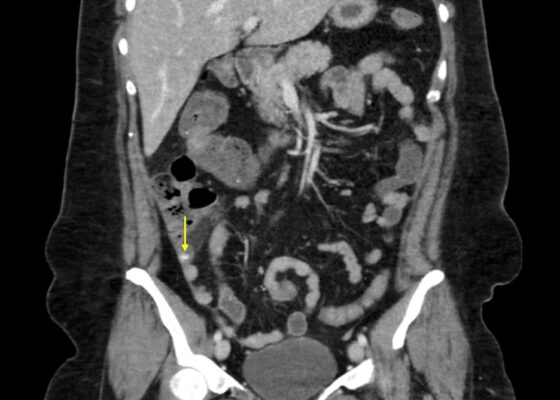
DOI: https://doi.org/10.5070/M5.52213Contrast-enhanced CT of the abdomen and pelvis was obtained. Coronal CT demonstrated a dilated appendix measuring up to 1.2 cm in diameter with multiple appendicoliths (yellow arrows), the largest measuring 1.1 cm. Mild periappendiceal fat stranding was present, consistent with acute appendicitis complicated by appendicoliths. The surrounding bowel and colon were normal in caliber and distribution. An additional coronal view demonstrated a dilated appendix (yellow arrow) containing an appendicolith with periappendiceal inflammatory changes. No evidence of perforation, abscess, or drainable fluid collection was identified.
Trapped In Transit – A Case Report of a Pediatric Gastric Bezoar Causing Intermittent Small Bowel Obstruction
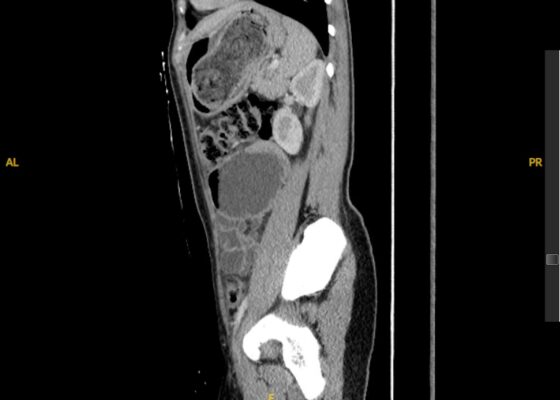
DOI: https://doi.org/10.5070/M5.52259The CT scan identified a heterogenous, mass-like lesion extending from the gastric fundus to the antrum, along with a small bowel obstruction (SBO) and significant small bowel dilation. An additional smaller heterogenous mass-like lesion was seen in the small bowel, causing the SBO. Given the mass-like lesion’s mixed attenuation and presence of internal air, a gastric bezoar was strongly suspected.

Clinical Decision-Making Case: Intussusception
DOI: https://doi.org/10.21980/J8.52171By the end of this mock oral boards session, learners will (1) demonstrate familiarity with the CDM case format and case play, (2) model a problem-based history and physical exam, (3) generate a differential diagnosis for pediatric abdominal pain, and (4) demonstrate the ability to manage intussusception.