
Ob/Gyn

Ruptured Hemorrhagic Ovarian Cyst Mimicking Ruptured Ectopic Pregnancy in a Post-Transplant Patient: A Case Report
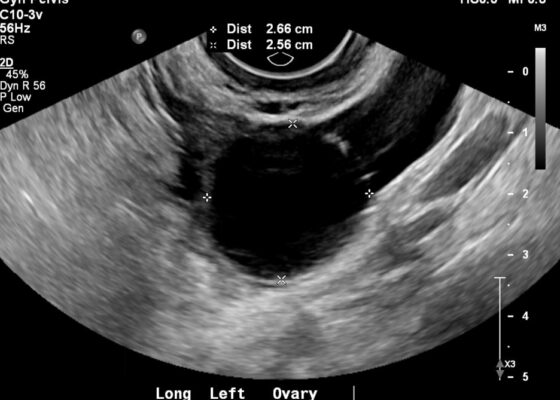
DOI: https://doi.org/10.5070/M5.52390A formal transvaginal ultrasound was ordered in the setting of the positive beta-hCG levels, which demonstrated a moderate volume of debris-containing free pelvic fluid layering in the posterior cul-de-sac (yellow highlighting), without sonographic evidence of an intrauterine gestational sac or yolk sac. Additionally, the left ovary contained a 2.8 cm cystic structure consistent with a hemorrhagic ovarian cyst (blue highlighting).
Point-of-Care Ultrasound Findings of Ovarian Hyperstimulation Syndrome: A Case Report
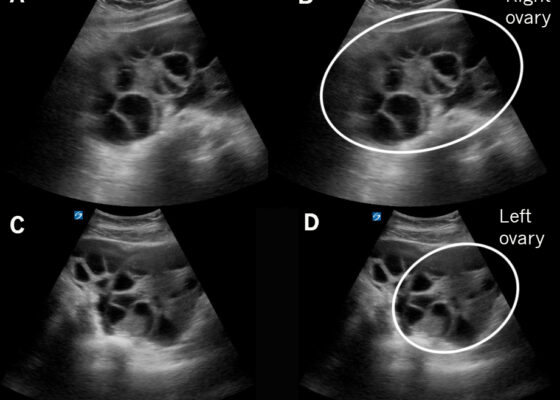
DOI: https://doi.org/10.5070/M5.52324Transabdominal POCUS in the right upper quadrant revealed clearly delineated pockets, the hypoechoic appearance being consistent with ascites, surrounding the liver and the gallbladder (Figure 1). A view of the left upper quadrant revealed a similar hypoechoic fluid collection that filled the space below the diaphragm and surrounded the spleen (Figure 2). A transabdominal pelvic view revealed enlarged ovaries, identifiable by the numerous, large, and well-delineated hypoechoic collections within that represent the enlarged follicles (Figure 3). The extent of the hypoechoic free fluid collections and the enlargement of the ovaries and their follicles is more apparent when viewed dynamically (Video).
Case Report on Rare Presentation of Intravenous Leiomyomas with Intracardiac Leiomyomatosis
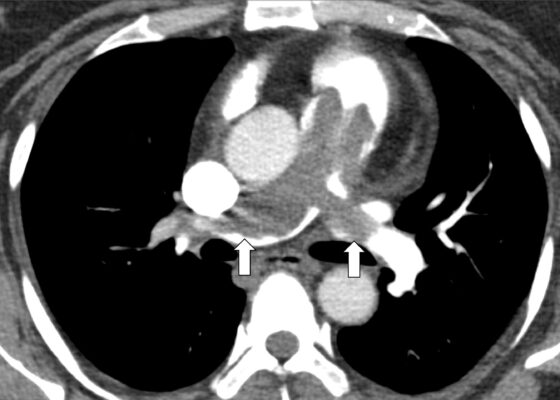
DOI: https://doi.org/10.5070/M5.52111Postoperatively, a CT of the abdomen and pelvis with contrast showed a lobulated soft tissue density (arrowheads) measuring 4.5 x 3 cm in the right pelvis. A subsequent MRI of the pelvis showed a 3.7 x 2.8 cm lobulated structure in the right pelvis above the vaginal cuff thought to be most consistent with an unusual cluster of venous structures. Following this, a CT venogram of the abdomen and pelvis revealed residual filling defects in the infrarenal IVC, extending through the right common iliac vein and multiple internal iliac branches.

Managing Spontaneous Abortion Hemorrhage: An Adult Simulation Case for Emergency Medicine Residents
DOI: https://doi.org/10.5070/M5.52263By the end of this simulation, learners should be able to: 1) recognize signs of post-abortion hemorrhage, 2) manage hemorrhage using appropriate physical maneuvers, uterotonic medications, and specialist consultation, 3) demonstrate proper placement of a Bakri balloon

Postpartum Complications Modified TBL
DOI: https://doi.org/10.5070/M5.52264By the end of this session learners will be able to: 1) identify the timeline in which postpartum complications typically occur, 2) discuss the specific differential diagnoses common in the postpartum period, 3) recognize risk factors for endometritis and mastitis, 4) recognize the presentation of postpartum cardiomyopathy and pituitary infarction, 5) formulate a treatment plan for postpartum endometritis including appropriate antibiotics and disposition, 6) formulate a treatment plan for mastitis including appropriate antibiotics and disposition, 7) formulate an appropriate assessment plan for pituitary infarction with appropriate disposition, and 8) formulate an appropriate treatment plan and disposition for postpartum cardiomyopathy.
A Woman’s Infertility Journey Complicated by Severe Ovarian Hyperstimulation Syndrome – A Case Report
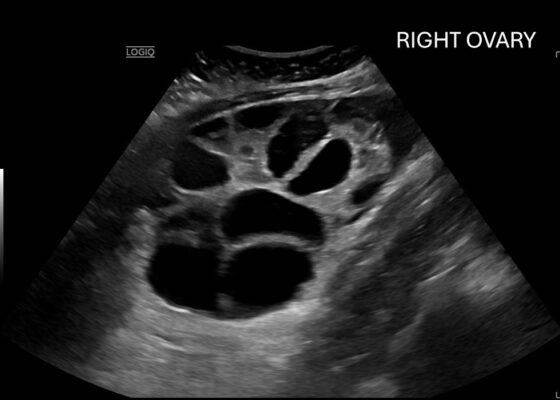
DOI: https://doi.org/10.5070/M5.52309Computed tomography (CT) of the abdomen and pelvis demonstrated pleural effusions in the lung bases (blue stars), ascites (blue stars), and enlarged ovaries with multiple cysts/follicles (white arrows). A formal pelvic US also demonstrated large volume ascites (white diamonds) and bilateral ovarian enlargement with numerous cysts. A CT angiogram (CTA) of the chest demonstrated small bilateral pleural effusions and no obvious pulmonary embolism.

Clinical Decision-Making Case: Pediatric Sexually Transmitted Infections and Consent
DOI: https://doi.org/10.21980/J8.52335By the end of this case the learner will be able to: 1) demonstrate competency with the new ABEM Certifying Exam Clinical Decision-Making Case format, 2) manage a simulated pediatric care encounter that requires navigating the details of pediatric consent, 3) explain common exceptions to requiring parental consent in emergency situations according to established guidelines as well as state and local laws, 4) report increased comfort managing ethical dilemmas related to pediatric consent in the ED.
Clinical Decision-Making Case: Seizing the Diagnosis: Eclampsia
DOI: https://doi.org/10.21980/J8.52338By the end of this Mock Certifying Exam session, learners should be able to: 1) demonstrate familiarity with the Clinical Decision-Making case format and structure, 2) elicit relevant historical information and connect that information to the diagnosis of eclampsia, 3) describe and interpret physical exam findings and their significance in establishing a pertinent differential diagnosis, which includes eclampsia, 4) initiate appropriate diagnostic testing, interpret results accurately, and formulate a stabilization and treatment plan for a patient with eclamptic seizures, and 5) reassess the patient's condition, modify the management plan as needed, provide relevant anticipatory guidance for disposition, and articulate the clinical decision-making rationale at each stage of the encounter.