
Visual EM
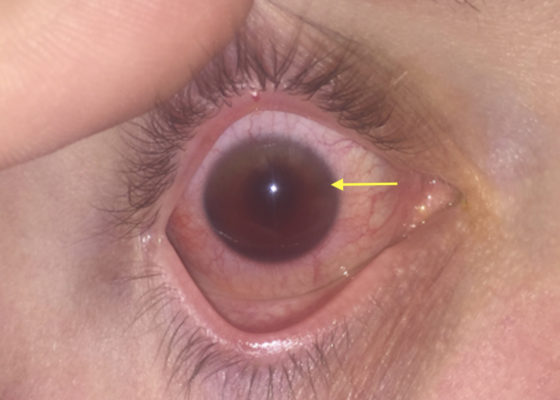

Traumatic Hyphema
DOI: https://doi.org/10.21980/J8Z04SUpon initial evaluation, the patient had an obvious hyphema in the right eye with associated conjunctival injection. Initially, the bleeding in the anterior chamber was cloudy just above the level of the pupil (yellow arrow), appearing to possibly be a grade II hyphema. There were no other signs of trauma to the eye under Wood’s lamp examination with fluorescein staining. The globe was intact. Intraocular pressure in the affected eye was 19 mmHg and 15 mmHg in the unaffected eye. Extraocular movements were full and intact. The pupil was 4 mm round and reactive to direct and consensual light. Visual acuity was greater than 20/200 in the affected eye compared to 20/25 in the unaffected eye. After an observation period of two hours, with the patient remaining upright, the hyphema had settled down to a rim in the lower anterior chamber (green arrow), a grade I hyphema.

Point of Care Ultrasound Illustrating Small Bowel Obstruction
DOI: https://doi.org/10.21980/J8T637POCUS of the small bowel illustrated significantly dilated loops of bowel (white line), thickened bowel wall (white arrow) and to-and-fro peristalsis, consistent with small bowel obstruction.
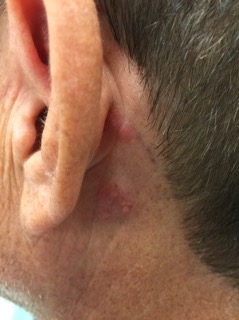
An Unusual Case of Pharyngitis: Herpes Zoster of Cranial Nerves 9, 10, C2, C3 Mimicking a Tumor
DOI: https://doi.org/10.21980/J8B05KOn exam, the patient was sitting upright while holding an emesis basin filled with saliva. His voice was noticeably hoarse. Examination of the head and neck revealed vesicular eruptions on the left scalp in the V1 dermatome and on the left mastoid process (Images 1 and 2). Physical exam also shows vesicular eruptions on the left posterior oropharynx that did not cross midline (Image 3).

Ramsay Hunt Syndrome
DOI: https://doi.org/10.21980/J85S7QLeft-sided cranial nerve VII palsy with flattened forehead creases, inability to keep the left eye open, and drooping of the corner of mouth. Vesicular lesions were found in and posterior to the left ear in a unilateral, dermatomal distribution.
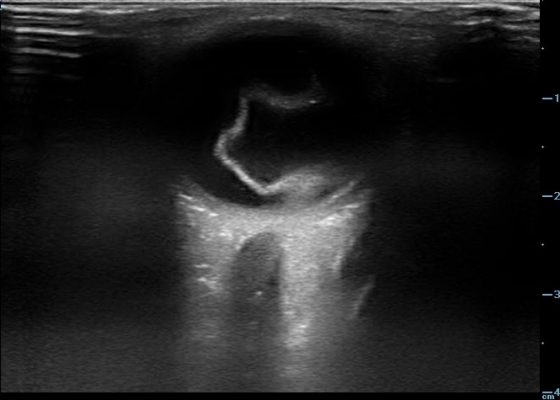
Retinal Detachment
DOI: https://doi.org/10.21980/J8204QBedside ocular ultrasound revealed a serpentine, hyperechoic membrane that appeared tethered to the optic disc posteriorly with hyperechoic material underneath. These findings are consistent with retinal detachment (RD) and associated retinal hemorrhage.

Necrotizing Soft Tissue Infection
DOI: https://doi.org/10.21980/J8X92TComputed tomography (CT) of the abdominal and pelvis with intravenous (IV) contrast revealed inflammatory changes, including gas and fluid collections within the ventral abdominal wall extending to the vulva, consistent with a necrotizing soft tissue infection.

Spontaneous Pneumomediastinum: Hamman Syndrome
DOI: https://doi.org/10.21980/J8NS72The initial CT scans showed extraluminal gas surrounding the distal esophagus as it traversed the posterior mediastinum, concerning for possible distal esophageal perforation that prompted surgery and GI consultations. There was no evidence of a drainable collection or significant fat stranding. The image also showed an intraluminal stent traversing the gastric antrum and gastric pylorus with no indication of obstruction. Circumferential mural thickening of the gastric antrum and body were consistent with the patient’s history of gastric adenocarcinoma. The shotty perigastric lymph nodes with associated fat stranding, along the greater curvature of the distal gastric body suggested local regional nodal metastases and possible peritoneal carcinomatosis.
The thoracic CT scans showed extensive pneumomediastinum that tracked into the soft tissues of the neck, which given the history of vomiting also raised concern for esophageal perforation. There was still no evidence of mediastinal abscess or fat stranding. Additionally, a left subclavian vein port catheter, which terminates with tip at the cavoatrial junction of the superior vena cava can also be seen on the image.

Intussusception
DOI: https://doi.org/10.21980/J8SH0WA segment of bowel within the right abdomen that measured approximately 1.6 x 1.5 cm transaxially. It demonstrated a hypoechoic edematous outer loop of bowel (blue arrow) and hyperechoic compressed loop of bowel telescoping within (red star), this is known as the "target sign."