
Visual EM
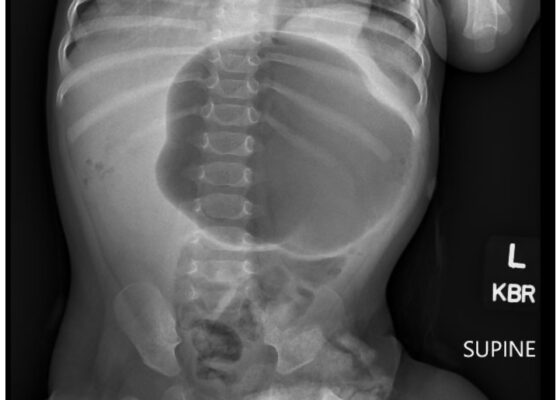

Case Report of Incarcerated Gastric Volvulus and Splenic Herniation in Undiagnosed Congenital Diaphragmatic Hernia in an Infant
DOI: https://doi.org/10.21980/J8VD27An upper gastrointestinal series (UGI) showed an enteric tube with its tip in the stomach and side-port in the esophagus. There was a large amount of air in the stomach and a small volume of scattered distal bowel gas. The tip of an enteric tube was seen in the stomach (red arrow). Contrast partially filled the stomach, and the greater curvature was visualized superior to the lesser curvature in the left upper quadrant (blue arrow). The body of the stomach was herniated into the right chest through a Bochdalek hernia (blue star). There was a large amount of air in the stomach and a small volume of scattered distal bowel gas. These findings were consistent with mesenteroaxial gastric volvulus.
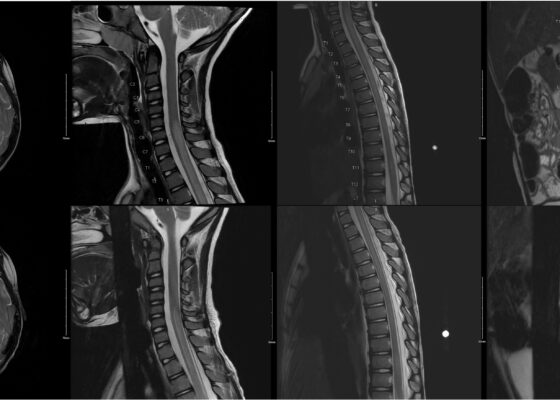
Beware of the Pediatric Limp: A Case of Mycoplasma Associated Acute Transverse Myelitis
DOI: https://doi.org/10.21980/J8QQ1QAn MRI with contrast, T2 sequence was performed. In Figures a-d, the MRI of the patient’s brain and spinal cord on admission shows abnormal signals in the patient’s pons (lack of symmetrical gray-white differentiation on cross-section) along with hyperintensity (sagittally shown as brightness in what should be homogenously intense spinal cord) and significant central cord edema (with swelling seen as increased width) starting from C5 and continuing to the conus medullaris around L1/L2.
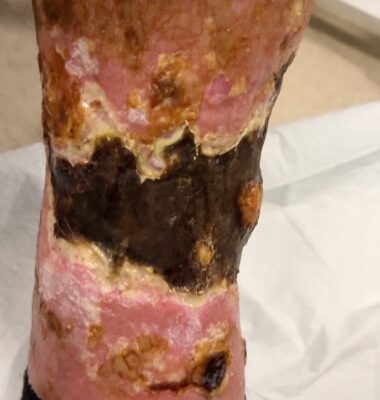
A Case Report of Calciphylaxis
DOI: https://doi.org/10.21980/J8KW8VOn arrival for this visit, the patient was nontoxic appearing with stable vital signs. The physical exam was notable for deep, ulcerated, bilateral anterior leg wounds with purulent drainage and large areas of eschar (see photographs).
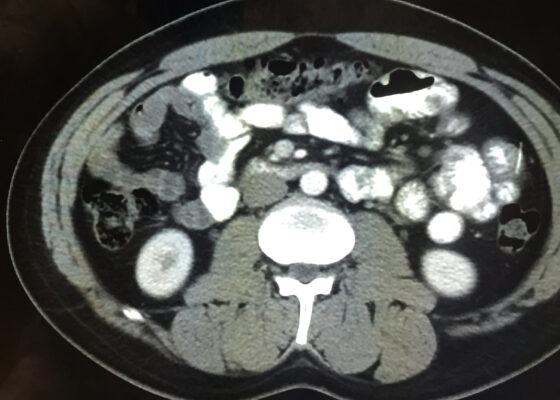
Case Report: Iatrogenic Bowel Perforation Following Dental Procedure
DOI: https://doi.org/10.21980/J8CD38The patient’s abdominal CT demonstrated a metallic foreign body in the left side of the abdomen within the small bowel, without surrounding induration or abscess. Radiology questioned whether the metallic foreign object perforated the bowel. Seen in the cross-sectional CT image, there is a hyperdense linear structure transversing the small intestinal wall, given that a portion of the structure was located outside of the lumen of the bowel.

A Case Report of an Unstable C-spine Fracture in the Emergency Department
DOI: https://doi.org/10.21980/J8SK90The initial workup in the ED showed an acute displaced fracture of the left occipital condyle (CT-coronal, fracture of the left occipital condyle, red arrow; displacement, orange line), a shattered left lateral mass with involvement of the vertebral canal (CT-axial, red arrow), and malalignment of the craniocervical junction (CT-sagittal, red outline). The CT angiogram head and neck showed a possible irregularity in the left vertebral artery. The CT head without contrast had no significant findings.

Eye-Opener: A Case Report of Eyelid Taping as Presenting Symptom of Myasthenia Gravis
DOI: https://doi.org/10.21980/J8NW8GPhysical exam was significant for a very pleasant, well-appearing female in no acute distress, noted to have clear plastic tape attached to her bilateral eyelids and brows (Image 1). When the tape was removed, she had bilateral ptosis, more significantly in the left eye (Image 2). She had no conjunctival injection or pallor. Her airway was patent and protected. She had no neck masses or carotid bruits. Her heart and lung exams were normal, with no evident respiratory distress. Her neurologic exam was further significant for limited extra-ocular movement (EOM). Her most notable deficits were with lateral and upward gaze (Video 1) indicative of weakness at the muscles innervated by cranial nerves III and VI. Her pupillary response was symmetric and brisk bilaterally. She had no additional cranial nerve deficits, slurred speech, or asymmetry in her strength or sensation throughout.

A Case Report of Inferior Rectus Abscess
DOI: https://doi.org/10.21980/J8J35GNon-contrast computed tomography (CT) imaging of the head in coronal, sagittal, and axial planes revealed a distinct 1.7 x 2.2 x 1.4 cm peripherally enhancing fluid collection within the left inferior orbit, involving the inferior rectus (yellow circle). This lesion resulted in restricted extraocular motility due to structural compression of the left globe. Laboratory results showed a mildly elevated white blood cell count of 11.5/mm3 and otherwise normal results including C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR).

A Case Report of Hydropic Gallbladder Presenting as Right Lower Quadrant Abdominal Pain
DOI: https://doi.org/10.21980/J8DD26Computed tomography (CT) of the abdomen and pelvis with contrast was ordered, and general surgery was consulted for the initial working diagnosis of acute appendicitis. However, the CT scan resulted with findings of a markedly distended gallbladder measuring approximately 14.5 x 4 centimeters (cm) with marked gallbladder wall thickening (magenta) and pericholecystic fat stranding (cyan). The appendix was not dilated and had no inflammatory changes or edema. Follow-up right upper quadrant ultrasound confirmed the diagnosis of acute cholecystitis.